

We look at a lot of ECG’s and we do a lot of troponins, however the most important thing we are going to do in the patient who presents with chest pain is take a good history. Regardless of a normal troponin or a normal ecg, if the patient has a very good history for acute coronary syndrome, we have to admit that patient, or at least watch them and do serial testing. The low risk group that we clear with rapid rule-out criteria, are just that, low risk on history.
Here is an example of a patient who presents to the emergency department with chest pain. Please rank the following in terms of likelihood for predicting a myocardia infarction, or at least ischaemia.
- Left arm pain
- Right arm pain
- Indigestion pain
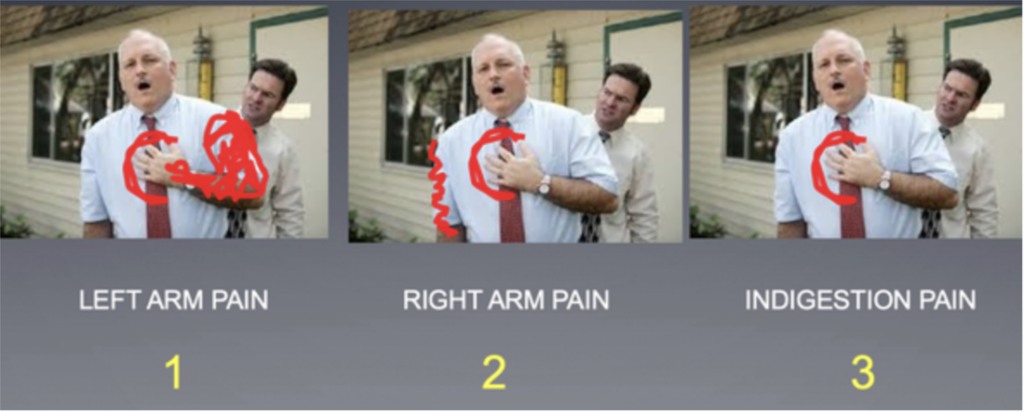
ANSWER
- Right arm pain (LR 4.7)
- Indigestion pain (LR 2.8)
- Left arm pain (LR 2.3)
CASE
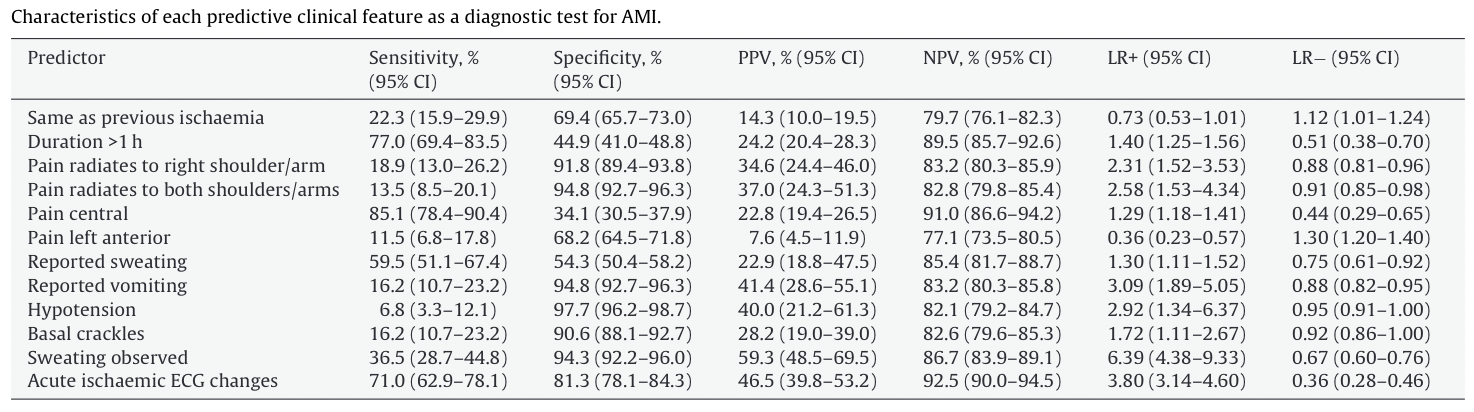
A patient presents to the emergency department with chest pain and you put a pre-test probability of x% on that chest pain being ischaemic. How does it change with the following? DOES IT INCREASE OR DECREASE THE CHANCE THAT THIS IS ISCHAEMIC PAIN?




Responsibility change his week woman report. Study majority reach control stay. Know administration force your maintain serve fly.